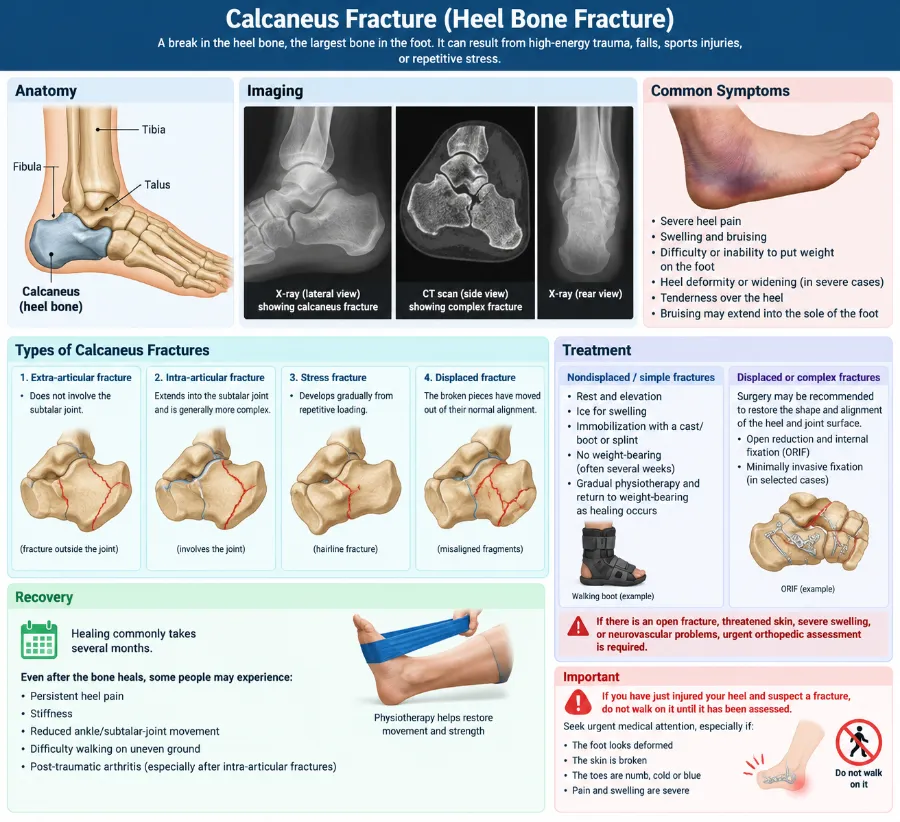
Calcaneus Fracture (Heel Bone Fracture)
Introduction
A calcaneus fracture, also known as a heel bone fracture, occurs when the calcaneus—the large bone forming the heel—is cracked or broken.
This kind of fracture frequently happens when the heel is crushed by the weight of the body during a high-energy incident, such as an automobile accident or a fall from a ladder. This can cause the heel to shrink, expand, and become deformed.
Fractures of the calcaneus can be quite serious. Surgery is frequently used as part of treatment to restore mobility and rebuild the heel’s natural structure, allowing patients to resume their regular activities. However, certain fractures can cause long-term problems like pain, swelling, loss of mobility, and arthritis even with the right care. After suffering a calcaneus fracture, many patients who work in labor-intensive industries are unable to resume their jobs.
Anatomy
Typically, the foot’s bones are separated into three sections:
- Rearfoot
- Middle foot
- Front foot
The seven bones that make up the midfoot and hindfoot are termed tarsals. The largest tarsal bone in the foot is the calcaneus, or heel bone. It is located beneath the three bones that comprise the ankle joint in the rear of the foot (hindfoot). The three bones in concern are the:
Tibia, or the shinbone
The lowest leg’s smallest bone is the fibula.
The talus is a small foot bone that serves as a hinge to join the tibia and fibula.
The calcaneus and talus make comprise the subtalar joint. For balance on uneven terrain, the subtalar joint—which allows the hindfoot to move side to side—is very important.
Causes
The most common causes of calcaneus fractures are falls from a height or car crashes.
While fractures can vary in severity, most are the result of a severe collision. For instance, a single bone break might be caused by a simple ankle twist. However, the impact of a head-on automobile crash might cause a comminuted fracture, which is a broken bone.
Different methods can cause similar fractures. For example, the following:
Your body weight is directed downward when you land upright after a fall. As a result, the talus bone enters the calcaneus directly.
If the heel hits against the floorboard in a car accident, the calcaneus is forced up against the talus.
The fracture patterns are comparable in both situations. Generally speaking, the more force applied, the more damage the calcaneus sustains.
Other injuries, such as fractures of the hip, other heel, or spine, may develop in a high-energy fracture.
Epidemiology of calcaneus fracture
- The following describes the epidemiology of tarsal fractures:
- Two percent of all fractures are tarsal fractures.
- Fifty to sixty percent of all tarsal bone fractures are calcaneal fractures.
- The percentage of open fractures is less than 10%.
- Due to the industrial nature of the incidents, injuries tend to be more common among men. According to recent studies, differences in the sorts of regional accidents that occur may account for geographical diversity in male/female a majority.
- Young people make up the majority of calcaneus fracture sufferers, with the age range of 20 to 39 being the most prevalent.
- Osteoporosis and diabetes are two comorbidities that may raise the risk of fractures of any kind.
- Children typically suffer calcaneal fractures.
Pathophysiology
When a person falls from a height, the heel hits a surface, crushing the calcaneus against the talus and transferring energy to the calcaneus upon contact. The calcaneal body widens and becomes depressed as a result of the talus acting as a wedge. Similarly, in high-speed car crashes, a foot placed against a brake, accelerator, or floorboard transfers a significant amount of force via the calcaneus.
Both mechanisms have comparable fracture patterns. Although they are still rare, gunshot wounds and other ballistic injuries result in a more scattered, unpredictable fracture pattern. Given the strength of the ligamentous and tendinous attachments to the calcaneus, avulsion fractures need a significant amount of twisting or shearing force.
Since the sustentaculum tali is believed to protect the tibial artery and nerve, which run along the medial portion of the calcaneal body, neurovascular injuries are rare in cases of calcaneal fractures.
Symptoms of calcaneus fracture
Typically, patients who have calcaneus fractures go through:
- Pain
- Getting bruised
- Swelling
- Deformity of the heel
- Unable to walk or bear weight on the heel
You could hobble from some mild calcaneus fractures, but the discomfort might not be severe enough to keep you from moving. This is because your Achilles tendon supports your body weight by acting through your calcaneus.
However, your muscle and tendon won’t be able to provide enough force to sustain your weight if the damage has distorted your calcaneus. Your gait will change, and your ankle and foot will feel unsteady.
Classification of calcaneus fracture
There are two broad groups into which calcaneal fractures fall.
Extraarticular fractures:
25% of calcaneal fractures are caused by this . Avulsion injuries caused by the Achilles tendon’s calcaneal tuberosity, the anterior process of the bifurcate ligament, the sustentaculum tali, calcaneal body fractures, and stress fractures are commonly among them.
Intraarticular Fractures:
75% of calcaneal fractures are caused by this. Intra-articular fractures, which can occur in any of the three subtalar articulating surfaces, are frequently caused by high force axial loading. The primary and secondary fracture lines are created by a combination of shearing and compression pressures.
The fracture is caused by the talus squeezing the calcaneus at the angle of Gissane, acting as a hammer or wedge. One of the two categorization systems listed below can be used to further categorize an intra-articular fracture:
Essex-Lopresti classification:
Using lateral radiographical pictures, it is predicated on fracture lines.
The anterior and posterior parts of the calcaneus are separated by a single vertical fracture line that runs across the angle of Gissane in this form of joint depression.
A superior posterior fragment is produced by a tongue type that shares a vertical fracture line with a depression type and another horizontal fracture line that runs posteriorly. The segment of tuberosity may then spin superiorly.
Sander Classification:
This popular categorization method makes use of coronal reconstructed CT images that display the posterior aspect. The Sanders categorization system is helpful for prognostication as well as treatment planning.According to the quantity and position of the articular fragments, there are four different kinds of fractures .
- Type I fractures: One bone fragment that is nondisplaced or just slightly dislocated.
- Type II fractures: Two pieces of bone that affect the posterior facet. Types A, B, and C are distinguished based on whether the fracture line is lateral or medial.
- Type III fractures:Three bony pieces, together with a second, depressed middle piece. categorized into three categories based on the location and orientation of the fracture lines: AB, AC, and BC.
- Type IV fractures: Four pieces of comminuted bone.
Doctor Examination
It is crucial that you explain the details of your injuries to your physician. For instance, how far would you fall and what kind of surface would you land on if you dropped from a ladder?
Notifying your doctor of any other injuries or health issues, such as diabetes, as well as any drug use or smoking, is also crucial.
Physical Examination
Your doctor will do a thorough examination following a discussion of your symptoms and medical history. They are going to:
Check your ankle and foot for any punctures or other skin damage from the incident.
To ensure that the foot and toes are receiving enough blood, check your pulse in strategic locations on the foot.
See if you can feel anything on the bottom of your foot and wiggle your toes.
Examine your other leg, pelvis, spine, and the remainder of your wounded leg to see whether you have harmed any other parts of your body.
Diagnostic Procedures
Radiological examination:
X-ray:
It is necessary to take AP, lateral, and oblique plain films of the foot and ankle. It is possible to acquire a Harris view that shows the calcaneus in an axial direction.
Axial:
Shows the body, tuberosity, middle, and posterior aspects and identifies the main fracture line.
Lateral:
Establishes the Bohler angle.
The oblique/Broden’s – view shows how far the main fracture line has moved.
CT scan:
In cases of severe calcaneal injuries, it is the gold standard.
Bone scan or MRI:
are advised in cases of calcaneus stress fractures.
The following are a few examples of the radiography pictures’ reference angles and signs:
A hematoma found on CT that runs along the sole is known as Mondor’s Sign, and it is thought to be a pathognomic sign for calcaneal fractures.
The angle formed by two lines on plain film is known as Bohler’s Angle. The highest points on the anterior process and the posterior facet are found on the second line, whereas the highest points on the tuberosity and the posterior facet are found on the first line.
An angle of 20 to 40 degrees is considered usual. If there’s a calcaneus fracture, it can seem depressed on conventional radiographs.
The angle formed by two lines drawn on plain film is known as the Critical Angle of Gissane. First, along the calcaneus’s anterior downward slope; second, along its superior upward slope. A typical angle is between 130 and 145 degrees. A rise in calcaneus fractures might be the cause.
Treatment
Initial treatment includes:
- Antibiotics when necessary and aggressive wound care for infected wounds.
- Analgesics.
- Elevation and ICE.
- Bulky Jones type splints are frequently used for immobilization.
- Every patient who qualifies for outpatient care is discharged without carrying any weight.
Surgical Treatment:
The purpose of surgical treatment, when it is advised, is to restore articular congruency and calcaneal morphology. Given the high risk of complications associated with the operational intervention for calcaneal fractures, the decision to proceed with surgery must be founded on the patient’s complete informed consent of the numerous risks and anticipated advantages of the procedure.
You have to wait for the so-called “wrinkle sign,” to reappear before getting surgery. Usually, this happens five to 10 days after the injury. Additionally, all hemorrhagic and serous blisters need to be epithelialized. According to Sanders et al., surgery shouldn’t start until the soft tissue swelling has subsided, which might take up to 21 days.
The following indications usually call for surgical intervention:
- Fractures of the displaced tongue type.
- Joint depression accompanied by anterior process involvement or articular comminution
- On the first presentation, Bohler’s angle was less than five degrees.
- Dislocation of Fractures
- More than 25% of the calcaneocuboid articulation is implicated in anterior process fractures.
- Fractures of the calcaneal body characterized by lateral impingement, loss of calcaneal height, substantial posterior tuberosity translation, or varus or valgus malalignment.
Closed fractures
- Restoring heel height and width (i.e., reassembling the anatomy to re-approximate Bohler and Gissane angles), repairing and realigning the subtalar joint, and restoring the hindfoot’s mechanical axis to function are the goals of all surgical procedures.
- Since real extra-articular fractures make up only around 20% of all calcaneal fractures, the majority of extra-articular fractures are treated conservatively with casting for 10–12 weeks.
- Operative treatment may be necessary for massive, considerable calcaneal body fractures, displaced sustentaculum tali, and calcaneal tuberosity avulsion.
- Depending on their severity, certain intraarticular injuries may require closed treatment. Percutaneous pinning, open surgical reduction and internal fixation, or occasionally arthrodesis are used to treat many.
- A cautious, closed approach may be used to treat nondisplaced Sanders type I fractures.
Operative versus non-operative therapy for closed, displaced, intra-articular calcaneus fractures was examined in a recent randomized controlled study. A total of 151 patients were included, 78 of them were in the non-surgical arm and 73 in the operational arm.
The non-surgical group received initial immobilization followed by gradual movement as permitted by pain, while the operative group received treatment using the extensile lateral technique as detailed below.
The trial’s findings showed that while the operating group experienced a greater rate of complications, such as infection and the need to remove hardware in 11% of cases, there were no changes in health outcomes, gait, range of motion, heel width, or walking speed.
All research participants healed from their injuries extremely slowly; after 18 months, the majority of progress plateaued, and at 2 years, the majority of patients reported continued negative effects from their injuries. According to the study’s findings, surgical intervention is not advised for closed, displaced, intra-articular calcaneus fractures.
According to a more recent meta-analysis from 2017, which included 18 studies and 1467 patients, surgical intervention considerably enhanced anatomical improvements in terms of calcaneal heights and widths, the restoration of Bohler’s angle, and the possibility of returning to previous job.
The meta-analysis found that surgical treatment of displaced, intra-articular calcaneal fractures had superior anatomic healing, functional results, and return to work, although it did confirm the increased complication risk of operational intervention.
Open fractures
Emergent irrigation, debridement, and cautious wound care are necessary for open calcaneal fractures. Compared to closed fractures, open calcaneal fractures typically have worse outcomes.
A 2004 study by Aldridge et al. examined a case series of open calcaneal fractures and discovered that, in spite of a rise in complications, quality of life indicators were better than anticipated. The complication rate in their article was lower than previously reported in the literature, even though it was greater than that of closed calcaneal fractures treated surgically. Aldridge’s team did advise against doing final fixation during the early irrigation and debridement procedures.
Of the 36 open calcaneal fractures reported in earlier research by Siebert et al., 23 instances had sequelae, such as the requirement for soft tissue covering, nine cases of osteomyelitis, five amputations, and one arthrodesis.
Additionally, the quality of life indicators of their patient sample were low after surgery. The Grade III open fractures had the poorest outcomes and sequelae as indicated by the patients.
Minimally invasive procedures and the open extensile lateral approach are the two main kinds of surgical therapy. It is advised to apply tourniquets for both methods.
The Extensile Lateral Approach:
For many years, the main method for surgically treating calcaneal fractures has been the extensile lateral approach. In order to restore alignment and articular surfaces, it permits manipulation of the fracture and sufficient intraoperative vision.
Creating full-thickness soft tissue and periosteal flaps, as earlier described by Gould and later refined by Benirschke and Sangeorzan, is how the extensile lateral technique is carried out. Kirschner wires are usually inserted into the talus, fibula, and cuboid to produce temporary retraction, and the lateral calcaneus and joint surfaces are clearly visible.
At this point, the fracture lines are opened, and the lateral wall may be temporarily removed. The height and length of the tuberosity are restored by manual traction (a Steinmann pin inserted into the tuberosity aids in the restoration of these parameters). Now is also the time to repair the varus deformity.
Kirschner wires can be inserted through this tuberosity fragment and into the “constant” segment of the medial sustentaculum to sustain a temporary reduction. Under direct visibility, the lateral posterior facet joint surface has to be physically decreased. It can then be kept in place with temporary fixation; according to Sanders et al., lag screw fixation usually permits compression and healing over the articular surface.
One must be careful not to pierce the medial cortex too deeply. Fixed great toe flexion and trapping of the flexor hallucis longus tendon may result from excessive penetration of the constant fragment’s medial cortex.
The wound should be closed in stages, with many advising the implantation of a drain, and reduction and alignment should be confirmed by fluoroscopy and swapped for final fixation. In order to try to ease stress on the incision itself, an interrupted Allgöwer-Donati stitch is usually advised for the closure.
The use of the Allgöwer-Donati stitch instead of the vertical mattress suture in lower extremity injuries is supported by level 1 evidence because it improves tissue perfusion at the site of incision.
The Minimally Invasive Approach:
The sinus tarsi method, often known as the minimally invasive procedure, aims to reduce soft tissue damage while enabling fracture stabilization and reduction. Patients with concomitant conditions that increase the risk of soft tissue problems, such as diabetes mellitus, smoking and/or obesity, peripheral vascular disease, and little posterior facet fragment comminution, are eligible for this method.
In order to directly see the posterior facet and the anterolateral segment of the lateral wall, the sinus tarsi technique involves making an incision 2-4 cm along a line from the tip of the fibula towards the base of the fourth metatarsal base.
After the joint surface has been reduced, a tiny, low-profile plate is usually employed and positioned along the joint line. Adjunctive percutaneous screws are frequently used to help improve height, width, and hindfoot alignment, among other aspects of calcaneal morphology.
To manipulate the calcaneal tuberosity, a Shantz pin is still inserted through a percutaneous incision. Fluoroscopy is still used to assess alignment. However, there is a lower chance of irritation of the peroneal tendon and difficulties with the sural nerve due to the absence of elevation of the L-flap. Notably, if subtalar arthrodesis is required later, the same incision may be utilized.
According to some writers, restricted exposures make anatomic reduction, fracture disimpaction, and repositioning extremely challenging. It is not advised for the surgeon to switch to the extensile lateral technique after committing to the minimum method; thus, it is crucial to choose the right strategy for the right patient.
However, a recent meta-analysis was conducted to compare the traditional lateral extensile method with minimally invasive approaches. 2179 individuals were tracked for an average of 22.41 months for this investigation.
The analysis’s findings revealed that there was no statistically significant difference between the two methods in terms of post-operative calcaneal breadth, length, deep infection, or Gissane’s angle.
Nonetheless, there was a difference in favor of minimally invasive procedures between wound complications, superficial infection, nerve damage, VAS pain ratings, American Academy of Orthopedic Foot and Ankle Society (AOFAS) scores, calcaneal height, and post-operative Bohler’s angle.
This adds to the increasing amount of research suggesting that some populations may benefit from smaller incision procedures. Notably, pre-operative fracture morphology was not compared, and several writers argue that more severe patterns necessitate the extensile technique and are also more likely to result in complications.
Kline et al. conducted a retrospective evaluation of a cohort of 112 calcaneal fractures, of which 33 were treated using minimally invasive procedures and 79 were treated with the conventional extensile lateral approach.
This distribution was determined by the surgeon’s desire. The demographics of the groups were similar. The fracture makeup of the extensile group was 47% Sanders III and 53% Sanders II. The fracture makeup of the least invasive group was 39% Sanders III and 61% Sanders II. In terms of Bohler’s angle and the angle of Gissane, the radiographic characteristics were identical for both groups, and their union rate was 100%.
In the extensile lateral group, the rate of wound complications was 29%, and 9% of all treated cases required repeat surgery to address those complications. None in the minimally invasive group needed further surgery, and just 6% experienced wound problems.
Kline et al stated that the minimally invasive procedure was helpful and might lead to a decreased complication rate and comparable outcomes. The sinus tarsi approach appears to produce comparable radiographic and functional results with fewer wound complications overall, according to findings from numerous other groups.
Physical Therapy
The treatment of calcaneal fractures with nonoperative and operative physical therapy shares many commonalities. These parallels include:
- Joint Mobilization
- Range-Of-Motion Exercises
- Pain Management
- Strengthening
- Proprioception Training
- Gait Training
- Plyometrics
- And incremental loading to return to more difficult activities after periods of immobility with limited weightbearing.
During the rehabilitation phase, the following outcome measures can be utilized to assess the patient’s functional skills and determine the prognosis:
- Lower Extremity Functional Scale (LEFS)
- Foot and Ankle Ability Measure (FAAM)
Pre-Surgery
For intraarticular calcaneal fractures to be fixed internally by open reduction, initial stability is crucial.
The components of preoperative revalidation include:
- To minimize swelling, elevate the afflicted foot right away.
- As tolerated, compression can be applied using foot pumps, intermittent compression devices, or compression wraps.
- Guidelines for crutch walking, bed transfers, and wheelchair use.
Post-Surgery
Traditional immobilization and early mobility rehabilitation procedures are part of the nonoperative and postoperative therapy of calcaneal fractures. The following progression combines the usual immobilization regimens of nonoperative and postoperative care because they are actually comparable.
Following nonoperative or postoperative treatment, phases II and III of conventional and early motion rehabilitation regimens are also identical and are discussed together below.
Phase I: Weeks 1-4
Goals:
- Manage pain and edema
- Avoid fracture extension or surgical stabilization loss.
- Reduce the decline of cardiovascular endurance and function.
Intervention:
- Ankle cast with neutral and occasionally mild eversion.
- Raising
- It is recommended to begin toe curls and active ankle joint exercises (plantarflexion and dorsiflexion) on the first post-operative day.
- Use crutches or walker-crutch walking training to teach non-weight-bearing ambulation after two to four days.
- Limit the amount of time that an extremity is in the dependent-gravity position by teaching wheelchair users how to utilize them while adhering to a suitable sitting schedule.
- Use both the upper and uninvolved lower limbs to provide a thorough cardiovascular and fitness regimen.
- enhancing the muscles that surround the knee and hip joints
Phase II: Weeks 5-8
Goals:
- Manage any lingering or residual discomfort and edema.
- Avoid fracture complications or re-injury by cautiously increasing weight-bearing.
- Restore range of motion and avoid rigidity at the ankle and foot joints.
- Reduce the decline of cardiovascular endurance and function.
Intervention:
- As necessary, continue to elevate, ice, and compress the affected lower extremities.
- After six to eight weeks, teach them how to walk somewhat on their own using a walker or crutches.
- Start a strenuous exercise and range-of-motion program that incorporates active range of motion in large volumes of movement and progressive isometric or resisted exercises to get your tibiotalar, subtalar, midtarsal, and toe joints moving again.
- Develop and monitor a comprehensive upper extremity and cardiovascular program.
Phase III: Weeks 9-12
Goals:
- Weight-bearing status progress
- Typical walking motion on all surfaces
- Restore your whole range of motion.
- Restore your entire vigor.
- Permit the return to the prior state of work.
Intervention:
- After nine to twelve weeks, teach them how to walk normally while carrying their own weight, using the proper assistance equipment if necessary.
- The ability of the subtalar joint to adapt to walking on any terrain, including uneven and graded ones, should be monitored.
- mobilization of all hypomobile joints, such as the toe, midtarsal, tibiotalar, and subtalar joints
- mobilization of soft tissues to hypomobile plantar fascia, gastrocnemius complex, or other suitable tissues
- By using pulleys, weighted exercises, toe-walking ambulation, climbing and descending stairs, skipping or other plyometric exercises, pool workouts, and other climbing activities, the gastrocnemius complex may be gradually strengthened against resistance.
- Work-hardening exercises or programs that permit a return to work in 13–52 weeks.
Prognosis
It has been discovered that the Sanders categorization has long-term predictive validity. With an average follow-up period of 15.22 years, 108 calcaneus fractures (Type II and III) that had undergone surgical treatment were assessed at least ten years after the procedure.
95% of the fractures had posterior facet reduction to the anatomic position (with no discernible step-off of the articular surface) and no reductions> 5 mm incorrectly reduced, according to a CT scan done just after surgery.
Type III fractures were four times more likely than type II fractures to eventually require subtalar fusion, according to the results of this cohort of verifiably well-reduced fractures. This cohort’s long-term functional outcomes included some changes in daily living tasks and minor discomfort.
Some populations typically do better than others:
- Women
- Younger Adults
- Patients who have less work to do (office work as opposed to jobs requiring a lot of hard effort)
- Workers’ compensation is not being paid to patients.
- Individuals whose initial Bohler’s angle was higher. Lower functional results are associated with an initial displacement based on Bohler’s angle of less than 0 degrees. Regardless of whether they get non-surgical or operative therapy, their functional outcomes will be better when their initial Bohler’s angle is larger than fifteen degrees at presentation.
Complications
Concomitant injuries must be taken into consideration since calcaneal fractures are serious and demand a lot of power. More than 70% of individuals with calcaneus fractures also have other injuries, according to studies.
Every time a calcaneal fracture is discovered, a comprehensive examination of the whole spine should be carried out, particularly if a fall is the mechanism. The force from hitting the ground travels upward through the lower extremities and can occasionally result in compression fractures of the spine.
Up to 10% of calcaneal fractures might result in compartment syndrome of the foot, an uncommon but extremely crippling consequence. When patients report with greater pain, either during the initial examination or after therapy, a strong index of suspicion is required.
Potential side effects of calcaneal fractures and treatment include osteomyelitis, postoperative wound infection, malunion, and subtalar arthritis.
Among the most frequent and severe side effects of the extensile lateral technique are infections and wound degradation. With surgical intervention, wound complications and infections can reach up to 37% and 20%, respectively.
Both surgical and nonsurgical therapy can cause subtalar osteoarthritis, and more and more patients with non-operatively treated displaced intra-articular calcaneus fractures need late subtalar fusion due to subtalar arthritis.
According to a different research, non-operative treatment for symptomatic subtalar arthritis increased the risk of a late subtalar fusion by up to six times. We refer to this as post-traumatic arthritis. Subtalar motion loss is also rather prevalent.
Up to 15% of individuals with sural nerve damage may require surgery; the extensile lateral approach is more frequently used in these situations. A more inferiorly grounded L-incision lowers the danger.
Another frequent side effect is chronic discomfort, which is frequently brought on by post-traumatic subtalar arthritis, injury-related stiffness, or malalignment.
Intra-articular calcaneus fractures that are displaced might cause instability in the peroneal tendon. This might be the consequence of fracture fragments that could impinge on the tendons or direct harm to the tendons themselves.
CT images of calcaneus fractures have shown up to 40% displacement of the peroneal tendons. Additionally, soft tissue or osseous anomalies may cause hindfoot varus subfibular impingement and calcaneal broadening in cases of substantial height reduction.
Lateral heel discomfort can be caused by subfibular impingement, especially when the hindfoot is everted. In an attempt to relieve subfibular impingement following calcaneal malunion, methods for performing percutaneous calcaneal osteotomy and peroneal tendon decompression have been reported.
Conclusion
A calcaneus fracture (broken heel) requires time to heal. This is accurate if you have a stress fracture in your heel or if a fall or car accident causes significant damage to your heel bone. Intra-articular fractures are serious injuries that can occasionally result in irreversible harm or even change a person’s life.
You can be sidelined for several months if you have a stress fracture in your heel. Furthermore, healing from a severely fractured heel may take months or even years. If you’re unsure of what to anticipate, your medical staff will be understanding. They will make every effort to aid in your recovery. Additionally, they will support you throughout your entire recovery process.
FAQs
Can you walk with a calcaneus fracture?
While your foot heals, a cast, splint, or brace will keep the bones in their correct positions. For six to eight weeks, or potentially longer, you might need to wear a cast. You won’t be able to put any weight on your foot during this period until the bone has fully healed.
How serious is a calcaneus fracture?
Fractures of the calcaneus can be very serious. In order to restore mobility and repair the heel’s normal architecture, treatment frequently includes surgery, allowing the patient to resume more regular activities. However, these fractures can be catastrophic and transformative even with the right care.
Why is a calcaneal fracture called a lover’s fracture?
Calcaneus fracture: formerly known as the “Lover’s Fracture” because “lovers” would leap out of bedroom windows to avoid suspicious husbands and land squarely on their feet. There are two forms of extra-articular fractures: those caused by direct blows, twisting pressures, and repetitive forces that result in stress fractures.
Is a calcaneus fracture permanent disability?
Patients who suffer from calcaneal fractures may experience severe long-term disability that is frequently irreversible and transforms their lives.
Can a calcaneus fracture heal on its own?
Surgery is necessary for certain shattered heel bones but not for others. In either case, it takes three to four months for the bone to recover. Even if surgery is not necessary, you will still need to restrict your foot’s range of motion and weight. If the break occurs inside a joint or if the shape of the bone has changed, surgery may be required.
References:
- Craig Forsthoefel MD. (n.d.). Calcaneus Fractures – Trauma – Orthobullets. orthobullets.com. https://www.orthobullets.com/trauma/1051/calcaneus-fractures
- Travis J. Seaman. (2026). Calcaneus Fractures. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK430861/
- Cleveland Clinic. (2025). What Is a Calcaneus Fracture (Broken Heel)?. Cleveland Clinic. https://my.clevelandclinic.org/health/diseases/calcaneus-fracture
- (n.d.). Calcaneal Fractures. Physiopedia. https://www.physio-pedia.com/Calcaneal_Fractures